What Matters to Expectant Mothers: Turning Behavioral Evidence into Market Growth

by Who Decides, What Matters | Series Topic 3 | Aug 28, 2026


For more than two decades, the Chief Medical Officer of a leading pediatric academic medical center advocated for a Women & Infants Tower that would integrate labor and delivery, the NICU, pediatric subspecialists, maternal-fetal medicine, and enhanced patient amenities. The proposal repeatedly stalled because the Board required credible evidence that the tower could generate enough incremental deliveries to justify hundreds of millions of dollars in construction costs. The central question was what matters most to expectant mothers when choosing where to deliver—something historical utilization data could not answer, since it reflected past choices rather than future switching behavior.

Traditional market research can identify what consumers say they value. Behavioral research will identify what consumers value through their decisions.

Finding What Matters

We surveyed women ages 18–44 across the metropolitan area who planned to have a baby in the future. The objective was straightforward: identify and prioritize the features that drive hospital choice for delivery.

We tested 14 attributes, and eleven were statistically significant drivers of choice. The behavioral results identified four categories of features with varying impacts on market growth: (1) priority, (2) modest impact, (3) must-haves, and (4) nice-to-haves. The graphic describes the specific features of the two categories that drive incremental market share.
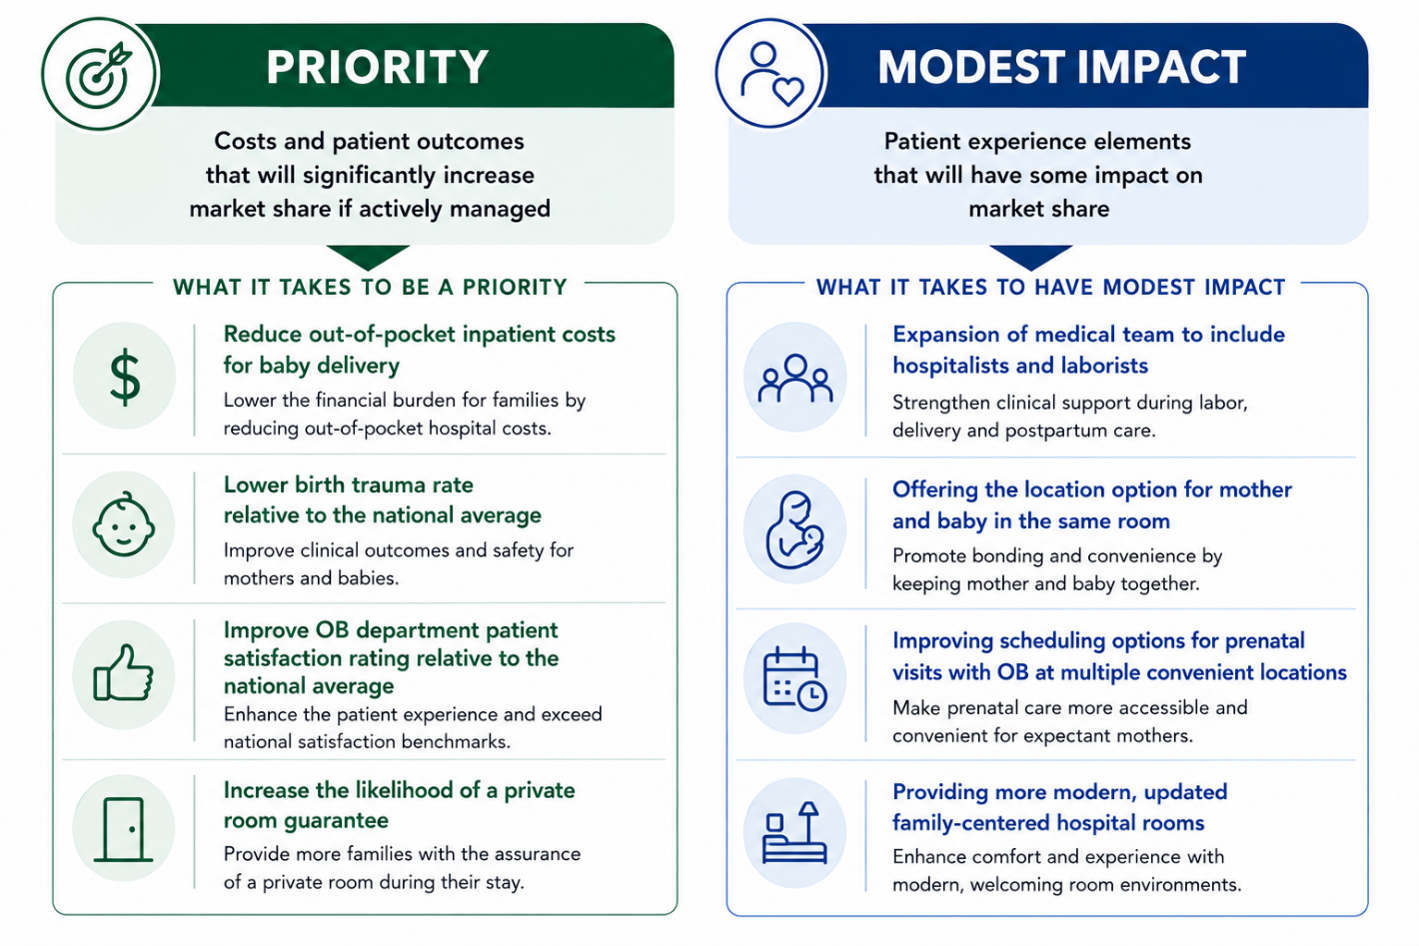
The third category, which we call must-haves, consists of services that women expect to be available at current levels. Failure to maintain this standard will result in a loss of market share. This category includes the following services:

  • Level III NICU plus pediatric subspecialities
  • Birthing and baby care classes
  • In-room sofa for spouse or partner

Just as important, several commonly considered amenities did not influence hospital choice. While “nice to have,” they are not services that the hospital should invest in heavily:

  • Designated parking for expectant mothers close to the hospital
  • Family food service available through the maternity ward
  • Enhanced data, voice, and video services

 The implication was clear: not everything that can be improved matters equally to the market.

From What Matters to What to Do

The behavioral model enabled the team to move beyond identifying drivers and to simulate how changes in those drivers could affect market share.

For example, reducing the birth trauma rate was projected to generate about 700 additional deliveries, and offering a 50% guarantee of a private room was projected to generate about 600 additional deliveries.

These scenarios transformed abstract consumer preferences into tangible business opportunities and provided leaders with a way to evaluate investments based on their likely market impact.

Based on behavioral evidence, the Mothers & Infants initiatives were projected to generate approximately 2,100 additional births and 750 NICU admissions annually at maturity.

The finding offered what traditional market research rarely does: confidence in what matters, how much it matters, and what will happen if the organization acts.

For healthcare leaders, that behavioral evidence became the foundation for Getting to Yes, providing the certainty needed to proceed with investment in the Mothers & Infants Center.
 

What Matters to Physicians When Capital Investment Depends on Future Physician Supply

In the recent Newsworthy article, "What Matters to Expectant Mothers: Turning Behavioral Evidence into Market Growth.", we presented findings that answer the question of what matters to consumers. Specifically, the article examined how expectant mothers choose where to deliver. The next question was whether the organization could recruit additional obstetricians to support the projected incremental volume.

The proposed center would combine the expertise of a world-class obstetrics service with full-spectrum pediatric subspecialty care. However, projected demand alone was insufficient to justify a major capital investment. Leadership needed evidence that they could attract enough obstetricians to support the business case—either through employment or voluntary alignment.

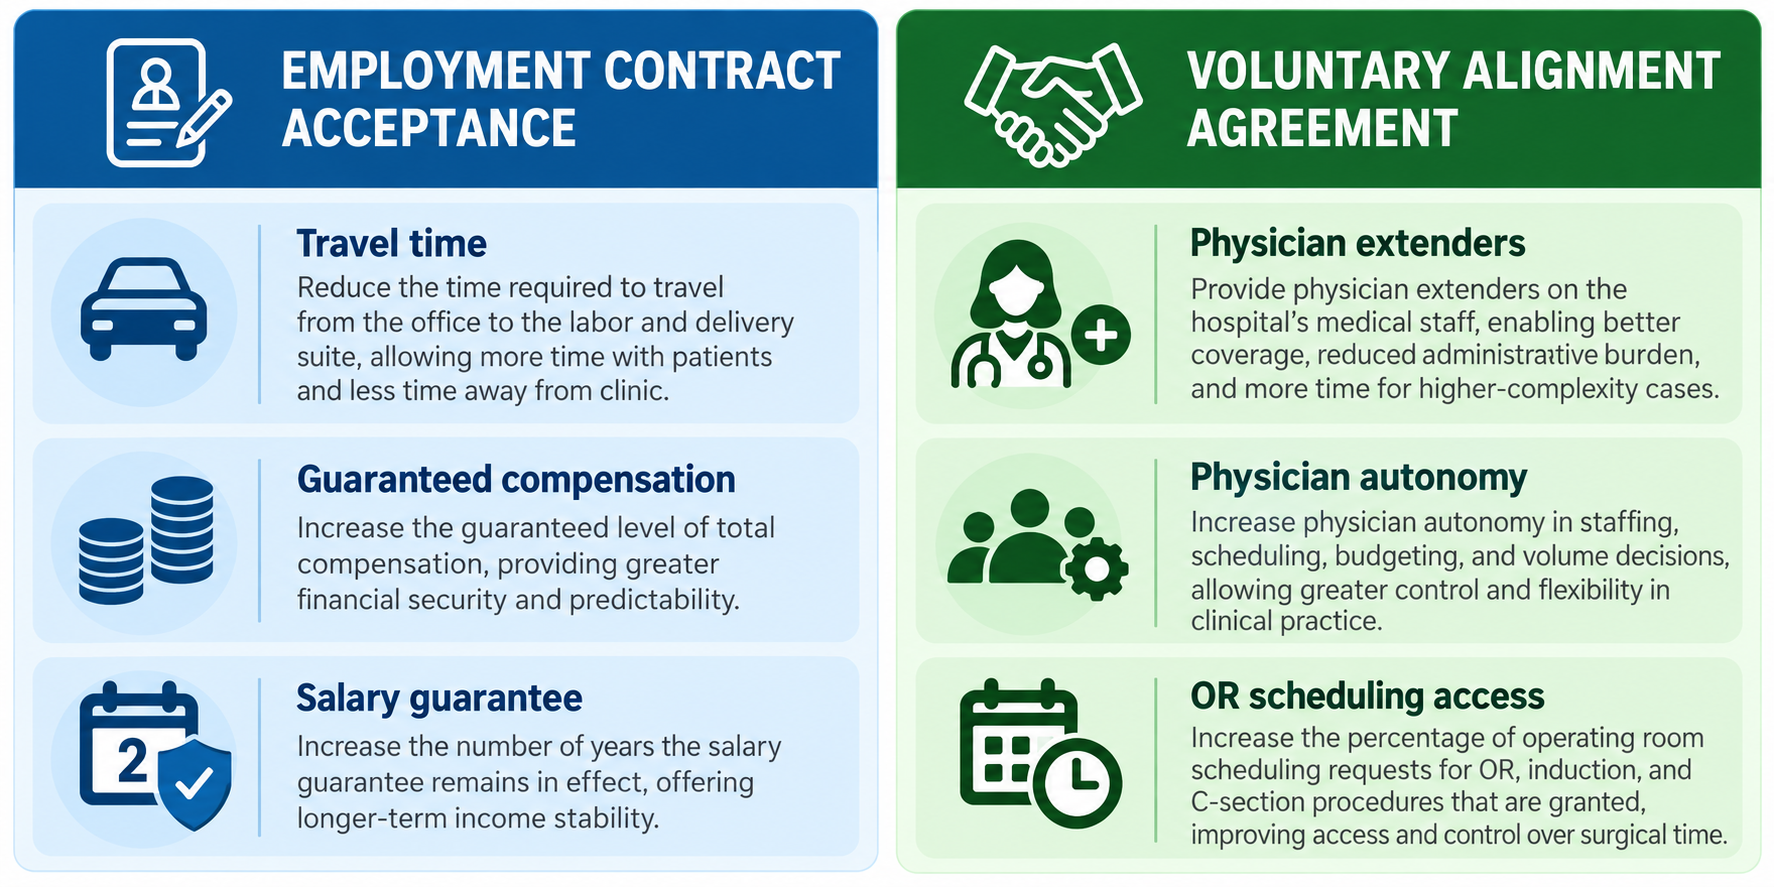
Rather than relying on historical recruitment patterns or stated intentions, which proved inadequate for predicting obstetricians’ interest in the new business model, MII designed two behavioral experiments to identify the drivers of obstetricians' decisions.  The two physician segments we tested were: (1) physicians employed by the center and (2) physicians who had privileges at the center (and were aligned)

Forty-two obstetricians participated in the employment contract acceptance experiment, and 48 in the voluntary alignment agreement experiment. Twelve features were tested, with ten in the employment model and seven in the alignment model.

The results identified specific priority drivers for each physician segment/group

From What Matters to What Changes Behavior

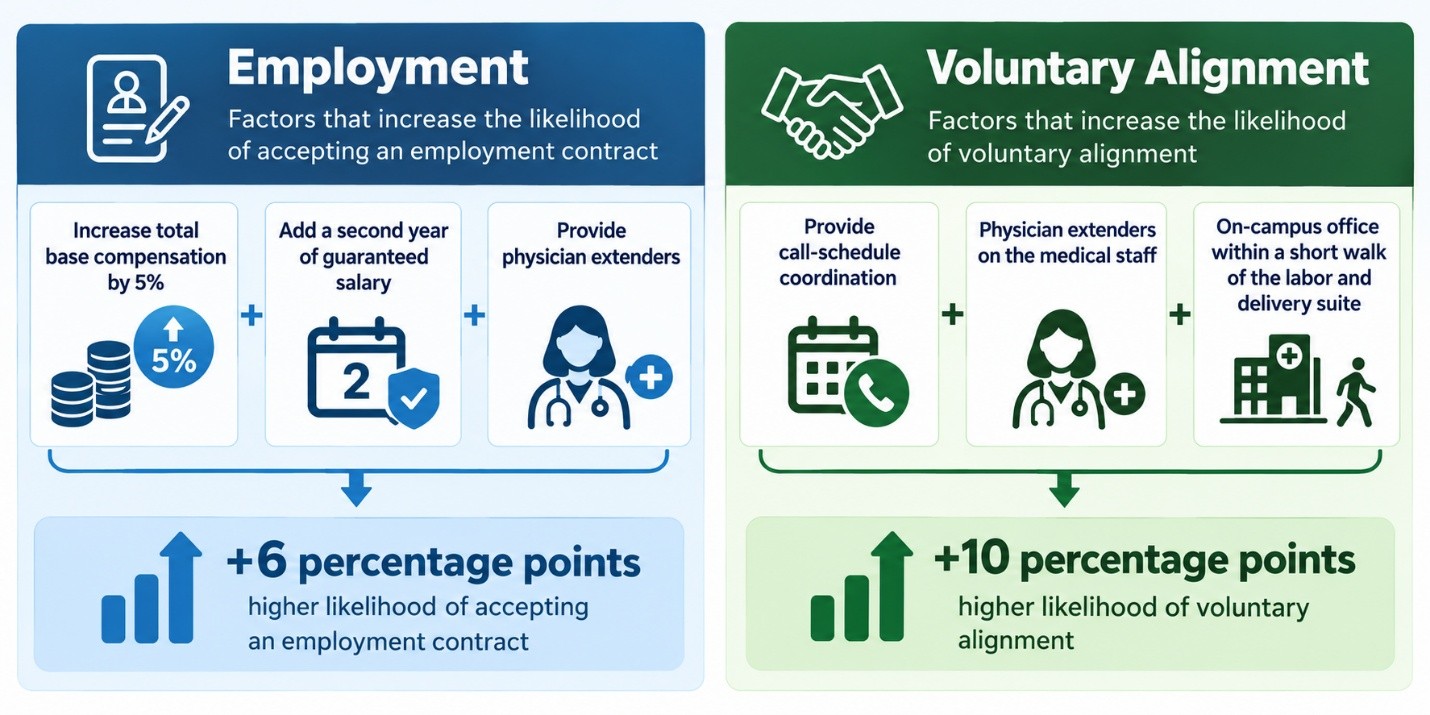
The behavioral research went beyond identifying what physicians said they valued. It quantified how changes to the proposed offers could affect the likelihood of acceptance. Among the scenario simulations tested, the following illustrative results are presented for the employment contract and the voluntary alignment scenarios.

These findings gave leadership what historical data could not: a way to assess how specific investment and contract decisions might influence behavior before committing capital.

Connecting Demand, Physician Supply and Capital

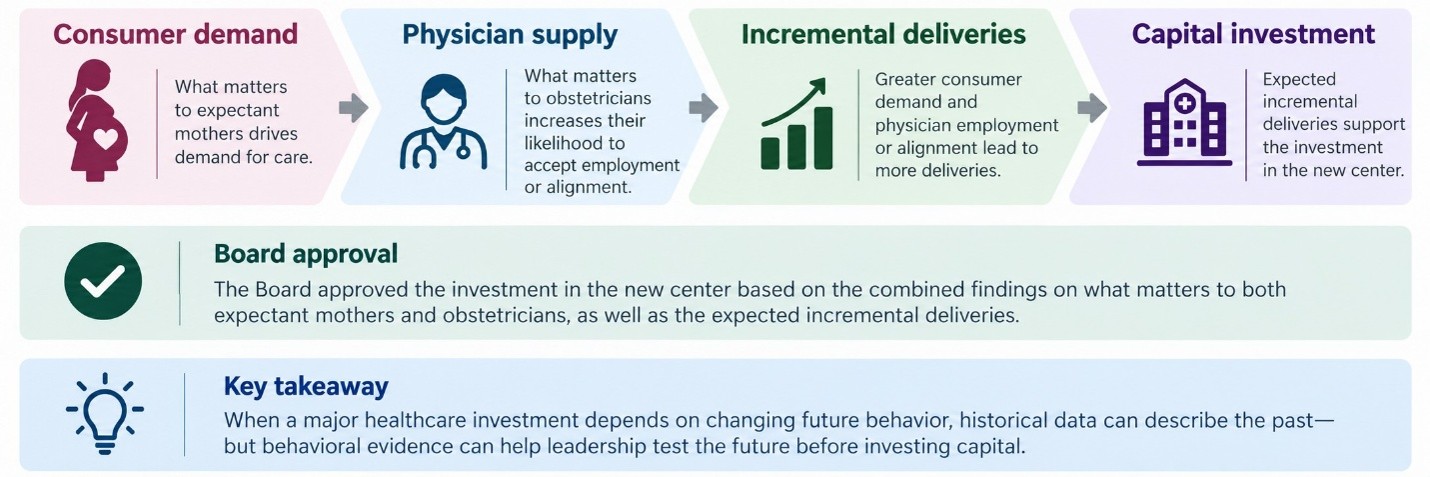
The truly powerful insights are derived from integrating the two physician experiments with the earlier consumer research (What Matters to Expectant Mothers).

While the expectant-mother’s study identified what matters to families when choosing where to deliver and quantified the potential for incremental deliveries, the obstetrician's study identified what matters to physicians when deciding whether to work with or align with the organization and quantified how changes to the employment and alignment agreements could affect participation. Thus, both sides of the supply and demand economic/business equation were considered.

This changed the nature of the Board's decision. The proposed center was no longer supported solely by historical utilization, financial projections, or assumptions about physician participation. Leadership had behavioral evidence showing what mattered to the people who would determine whether the center could succeed—and how changes to the proposition could influence their decisions.

Learning extends beyond this center: when a major healthcare investment depends on changing future behavior, historical data can describe the past—but behavioral evidence can help leadership test the future before investing capital.

_________________________________________________________________________________

Mi4Sight® is Market Innovations, Inc.’s behavioral economics modeling solution. Built on more than 20 years of experience and 135 healthcare studies, it helps leaders test innovative hypotheses, quantify likely behavior, and evaluate investments before committing capital.

To learn more, visit Mi4sight | Market Innovations Inc.